Treated by Dr. Moode Jayanth at Dr Jayanth Moode
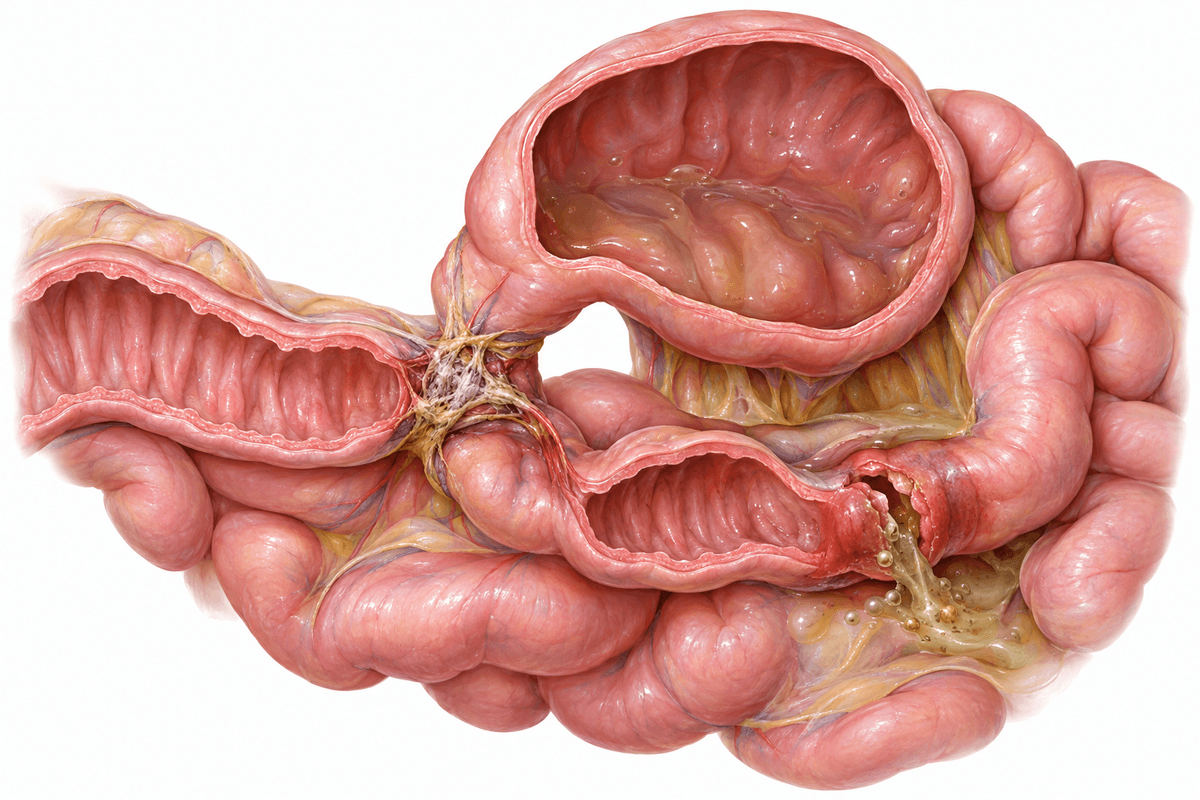
Intestinal obstruction occurs when the normal movement of food and digestive contents through the bowel is blocked. Perforation is a hole or tear in the intestinal wall that allows contents to leak into the abdominal cavity. Both conditions require urgent medical attention and often surgical intervention.
Blockage in the small intestine, often caused by adhesions from previous surgery, hernias, or tumours. May be partial or complete.
Blockage in the colon or rectum, commonly due to tumours, volvulus (twisting), or strictures. Typically develops more gradually than small bowel obstruction.
A hole or rupture in the intestinal wall allowing bowel contents to leak into the abdomen, causing peritonitis. May occur with or without pre-existing obstruction.
Multiple factors can contribute to the development and progression of this condition.
Recognising the signs early gives you more treatment options.
Assessment begins with clinical history and physical examination to identify signs of obstruction or peritonitis. Imaging and laboratory tests help confirm the diagnosis and guide management, though not every patient requires all investigations.
From conservative to surgical — we always start with the least invasive option first.
A structured, patient-first approach from first visit to full recovery.
Dr Jayanth Moode evaluates the severity through clinical examination, reviews imaging findings, and determines whether immediate surgery is needed or if initial stabilisation is appropriate.
Fluid resuscitation, electrolyte correction, nasogastric decompression, and antibiotic cover are initiated. The patient and family are informed about the diagnosis and treatment plan.
When surgery is required, Dr Jayanth Moode performs the necessary procedure to relieve obstruction, repair perforation, and remove non-viable bowel. The approach is individualised based on operative findings.
Close monitoring continues after surgery with attention to fluid balance, pain control, return of bowel function, and wound care. Nutritional support and mobilisation are introduced as recovery progresses.
What to expect at each phase of recovery.
Patients typically remain in hospital with intravenous fluids, pain management, and gradual reintroduction of oral intake as bowel function returns. Duration varies based on the extent of surgery and individual recovery.
Once bowel function resumes and the patient tolerates diet, discharge home is planned with instructions on wound care, diet advancement, and activity. Follow-up appointments monitor healing and address any concerns.
Full recovery may take several weeks to months depending on the underlying cause and extent of surgery. Some patients may require ongoing management of the underlying condition or management of stoma if created.
Successful surgery aims to restore normal bowel passage and resolve the acute emergency. The underlying cause is addressed where possible, though some conditions may require ongoing management.
Prompt treatment seeks to prevent serious complications such as bowel strangulation, sepsis, and multi-organ failure. Early intervention generally improves outcomes, though individual results vary.
Adhesions may reform after surgery, and some patients face a risk of future obstruction. The likelihood depends on the underlying cause and individual factors.
Most patients return to normal activities after recovery, though those requiring stoma or with ongoing bowel conditions may need adjustments and continued support.
Untreated intestinal obstruction can progress to bowel strangulation, where blood supply is cut off, leading to tissue death. Perforation allows bacteria and bowel contents to spill into the abdomen, causing peritonitis and sepsis. These complications can be life-threatening and require emergency surgical intervention.
Seek immediate medical attention if you experience severe, persistent abdominal pain, inability to pass stool or gas, repeated vomiting, or significant abdominal distension. If you have a rigid, tender abdomen, fever, or signs of shock such as rapid heartbeat and dizziness, go to the emergency department without delay.
Early treatment means more options and better outcomes. Book a consultation to understand your condition and explore the right path forward.